
There is no human trial of ayahuasca for fibromyalgia. There is no human trial of ayahuasca for any kind of chronic pain. As of September 2026 the published evidence is 29 preclinical studies, almost all of them in rodents, plus 1 case report about a different brew. That is the whole file.
I co-founded an ayahuasca center on the Río Momón. Saying that out loud is bad for business. I’m saying it anyway, because the pages ranking above this one either borrow psilocybin’s trial results without admitting it, or point at “studies” they never name.
Below is what exists, why the medication you’re probably taking matters more than any of it, and what I’d want to know if I were the one reading this with widespread pain.

What does the research on ayahuasca and fibromyalgia consist of?
It consists of animal studies. In July 2025 a team at the University of São Paulo published the only systematic review of ayahuasca, pain and inflammation that exists. They found 29 studies: 6 looking at pain responses, 23 at inflammation. Most were rodent models. 4 were cell cultures. 1 was a plant.
By compound, harmine appeared in 16 of them, harmaline in 5, DMT in 4, tetrahydroharmine in 1, and the whole brew in 3. The pain tests were things like the hot plate, the tail flick and sciatic nerve ligation. Those are mice.
The review’s own summary is careful: “Although ayahuasca pain-related investigations are scarce, existing findings are encouraging.” It closes by asking for “human studies using pain models” to confirm whether any of it carries over. It identifies no human trial in pain or in fibromyalgia, because there isn’t one.
One of its authors said the same thing in a round table interview: his group has started with a healthy population, and wants to run a clinical study in people with chronic pain, headaches or fibromyalgia, in what he called the not-too-distant future. That is a researcher who co-wrote the review confirming the trial is still ahead of us.
Where the pain claims actually come from
They come from psilocybin. Its trial results keep getting attached to ayahuasca, and the anecdotes people repeat are real even when the evidence behind them isn’t.
The 2026 review of classic psychedelics for chronic pain in the journal Drugs counts the entire controlled evidence base: 2 small migraine trials at 10 and 18 participants, a cluster headache trial at 16, and 1 open-label fibromyalgia pilot with 5 people run at the University of Michigan. Every one of those used psilocybin.
That pilot is the study you’ll see quoted. 5 women, no control group, unblinded, 15 mg then 25 mg of psilocybin with 6 therapy sessions around it. Pain severity dropped by 2.3 points at 1 month. The authors list their own limitations first: no control arm, a sample of 5, and entry criteria strict enough that they say it may not carry over to ordinary fibromyalgia patients.
It’s a real result. It isn’t about ayahuasca, and a center that lets you think otherwise is selling you something.
The closest human datapoint involving the same alkaloids is a single 2019 case report about changa, which is DMT combined with beta-carbolines from Syrian rue. Same enzyme action as the vine. Different plant, smoked instead of drunk, 1 patient, no control group. I’m not going to build a page on it.
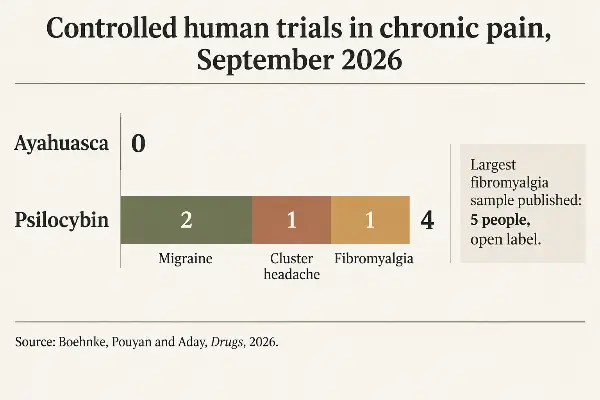
How ayahuasca and psilocybin compare on the evidence
Psilocybin is several years ahead, and it is not close. Here is the count as it stands in September 2026.
| Ayahuasca | Psilocybin | |
|---|---|---|
| Controlled human trials in chronic pain | 0 | 4 (2 migraine, 1 cluster headache, 1 fibromyalgia) |
| Human trials in fibromyalgia specifically | 0 | 1 published, 3 more running |
| Published human case reports in pain | 0 (1 for a related brew) | Several, plus survey data |
| Preclinical pain studies | 6, in the 2025 systematic review | Larger literature |
| Preclinical inflammation studies | 23, in the same review | Larger literature |
| Largest fibromyalgia sample so far | None | 5 people, open label |
Read the right-hand column carefully before you get excited about it. The largest published fibromyalgia sample in this entire field is 5 people with no control group. That is the state of the art, and it belongs to a different medicine from the one we serve.
Does your fibromyalgia medication rule you out?
Often, yes, and this is the part almost nobody expects.
Duloxetine and milnacipran, the 2 drugs most associated with treating fibromyalgia, are SNRIs. Amitriptyline is a tricyclic. Tramadol is serotonergic. The caapi vine works by inhibiting monoamine oxidase, which is also what the brew does in the brain, and that inhibition is what turns those drugs into a serotonin syndrome risk rather than a footnote.
So for a lot of people with fibromyalgia the question was never whether ayahuasca works. It’s whether they can safely come off the thing their rheumatologist put them on, for 6 weeks, before they even fly. Some can, with their prescriber running it. Some shouldn’t try.
We’re not unusual in applying that rule. Imperial College London’s own psilocybin fibromyalgia study excludes anyone taking SSRIs, SNRIs, tricyclics, antipsychotics or mood stabilizers. The researchers set the same bar we do. The Drugs review names MAO inhibition with ayahuasca among the interactions clinicians have to manage.
Our full timelines, and the story of the night in 2018 that produced them, are in our guide to the dieta and the medication rules. The short version: our medical director reviews every intake form inside 72 hours and speaks to your own prescriber directly before any taper starts. We won’t ask you to stop a medication behind your doctor’s back.
Pregabalin, gabapentin and low-dose naltrexone don’t act on serotonin the way those drugs do. They’re common in this population and they come up constantly, so ask us directly rather than assuming either way.

Can you lie on a mat for 6 hours with fibromyalgia?
Physically, most people can, and nobody in this industry seems willing to describe what it involves.
A ceremony here starts around 8:30 in the evening and most people are still in the maloca past 2 in the morning. You’re on a mat on a wooden floor in total darkness. There’s no electricity in that building, ever. You can sit up, lie down, shift position, or step outside with a facilitator. You cannot get up and walk it off in the middle of the peak and come back to where you were.
For our first 2 years we used thin foam pads. Guests told us they caused back pain, so in 2021 we replaced every one of them with proper mattresses. Small thing. It’s also the only honest answer I have to this question, and it came from people complaining rather than from anything clever on our part.
Plant baths, 2 to 4 across the retreat, are prepared individually by our healers and several guests describe them as the most physically comfortable part of the 10 days. I’m not going to claim they do anything for pain.
If lying still for 6 hours is the part you’re worried about, read the hour-by-hour breakdown of a ceremony before you apply, not after. The structure of the 10 days is set out in full as well.
Nobody here comes for pain
We record why people come. Across roughly 1,900 guests in 9 years it breaks down like this.
| Reason for attending | Share of guests |
|---|---|
| Depression and anxiety | 30% |
| Trauma and PTSD | 24% |
| Addiction recovery | 15% |
| Grief and loss | 11% |
| Spiritual seeking and personal growth | 11% |
| General life transition | 9% |
Chronic pain isn’t on that list. We don’t have a category for it.
I could have left that out. It’s the most useful thing on this page if you have fibromyalgia, because it tells you something no testimonial will: you’d be unusual here, and most of the people around you in the circle would be working on something else.
It also means there’s no outcome data to show you. Our follow-up measures depression and PTSD scores, including the 30% of guests whose improvement didn’t hold. Pain isn’t one of the things we measure, so we can’t tell you anything about it, and anyone who can’t name their instrument isn’t showing you a result.

What I’d want to know if this were me
4 things, in order.
Ask your prescriber about the taper before you ask any retreat about availability. That conversation decides most of this and it has nothing to do with which center you pick.
Treat any page that quotes a pain statistic at you as a page borrowing psilocybin’s data. Ask which study, and in which species.
If a center says yes to you quickly, that tells you about its screening rather than its hospitality. We turn away 13% of applicants outright, and the reasoning is set out in our piece on what actually decides your risk.
And be honest with yourself about what you’re hoping for. Ayahuasca has reasonable evidence behind it for depression and for trauma. That’s why most people are in the room. If pain has brought depression with it, the depression is the part with research behind it, and that is a different sentence from the one on most retreat websites.
You can read how this place began if you want to know who you’d be dealing with. And if you want a straight answer to a specific question before applying, we’d rather have that conversation than take a booking we should have declined.
FAQs
Is there any research on ayahuasca for fibromyalgia?
No human trial exists. The only systematic review of ayahuasca, pain and inflammation, published in July 2025, identified 29 preclinical studies, of which 6 examined pain responses. Almost all were rodent models, with 4 in cell cultures. The review’s authors call for human studies to test whether any of it translates.
Can you drink ayahuasca if you take duloxetine or milnacipran?
Not while you’re taking them. Both are SNRIs, and the caapi vine inhibits monoamine oxidase, which makes the combination a serotonin syndrome risk. We require a minimum 6-week taper supervised jointly by our medical director and your own prescriber. Some people shouldn’t attempt that taper, and that decision belongs to your prescriber.
Does ayahuasca help chronic pain?
Nobody can answer that from human data yet, because no human trial has been run. Animal studies have found pain-response and anti-inflammatory effects for harmine and DMT, and there are self-reports from people who have used psychedelics for pain, but self-reports are not trial results and mice are not people.
Is a fibromyalgia diagnosis itself a disqualification?
No. Fibromyalgia is not on our list of automatic disqualifications. The medication you take for it may be, which is a different question and the one that decides most applications.
Is psilocybin further along than ayahuasca for fibromyalgia?
Yes, clearly. A 5-person open-label psilocybin pilot was published in 2025 and further trials are running at Imperial College London, the University of Alabama at Birmingham and Maastricht University. Ayahuasca has none. Any claim that puts the 2 on the same footing is borrowing psilocybin’s evidence.
How many guests come to your center for chronic pain?
Chronic pain is not one of the 6 reasons we record. Across roughly 1,900 guests the categories are depression and anxiety 30%, trauma and PTSD 24%, addiction recovery 15%, grief and loss 11%, spiritual seeking 11%, and life transition 9%. We have no pain outcome data because pain is not something we measure.